Elderly Care Explained: Comparing Providers in Assisted Living, Independent Living, and Nursing Homes
Business Name: BeeHive Homes of Volcano Cliffs
Address: 6230 Montaño Rd NW, Albuquerque, NM 87120
Phone: (505) 302-1919
BeeHive Homes of Volcano Cliffs
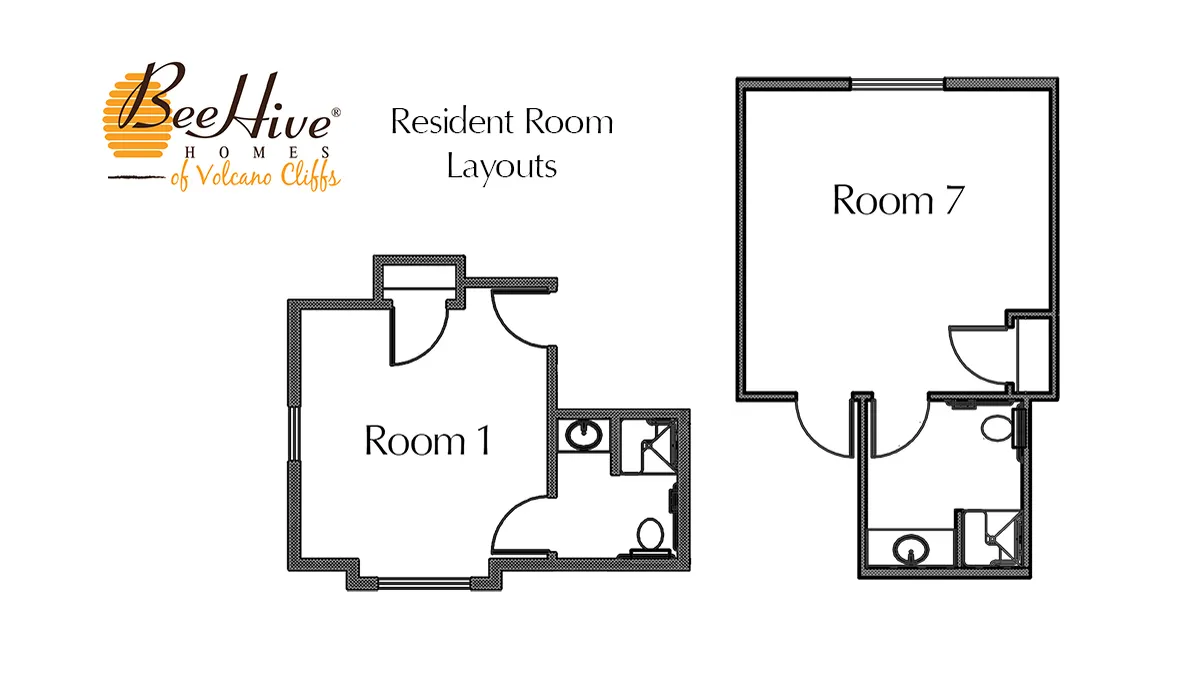
At BeeHive Homes of Volcano Cliffs, New Mexico, we offer the finest assisted living experience available in a cozy, comfortable homelike setting. Each of our residents has their own spacious room with an ADA approved bathroom and shower. We prepare and serve delicious home-cooked meals three times a day every day. We maintain a small, friendly elderly care community. We provide regular activities that our residents find fun and contribute to their health and well-being. Our staff is attentive and caring and provides assistance with daily activities to our senior living residents in a loving and respectful manner. We would like to invite you to tour and experience our assisted living home and feel the difference.
6230 Montaño Rd NW, Albuquerque, NM 87120
Business Hours
Choosing the ideal setting for an older grownup is one of those decisions that feels both immediate and overwhelming. Families typically call me after a fall, a hospitalization, or an abrupt scare, and the first sentence is usually the same: "I don't even understand where to begin."
The difficulty is that we use "senior care" as if it were one thing. It is not. Independent living, assisted living, nursing homes, and respite care all serve extremely various purposes. When you comprehend what each succeeds, and just as significantly what it does refrain from doing, the path forward ends up being clearer.
This guide strolls through how these settings compare in daily truth, not simply on glossy sales brochures. The goal is to assist you match a real individual, with real strengths and restrictions, to the right level of support.
How the primary senior care settings differ in practice
On paper, the differences look tidy. Independent living is for active elders. Assisted living includes assist with daily tasks. Nursing homes supply 24/7 skilled nursing. In truth, the lines blur, and every structure has its own culture.
It helps to think less about labels and more about 3 axes:
- How much hands on aid with daily activities is available.
- How much medical oversight and tracking exists on site.
- How much control the person keeps over their schedule and lifestyle.
Each kind of elderly care balances those 3 elements differently.
Independent living: way of life initially, support second
Independent living neighborhoods are frequently the first formal step in senior care, though lots of residents do not believe of them as "care" at all. They see them as a more secure, simpler way to live without the burden of home maintenance.
These communities normally provide private apartment or condos, common dining, house cleaning, maintenance, arranged transportation, and a calendar of social and wellness activities. Staff exist, however they are not there to provide hands on personal care.
From the resident's viewpoint, independent living feels closest to routine home life. They lock their own door, choose their own regimens, and decide which services to utilize. The safeguard is lighter: pull cords, emergency pendants, and staff who can respond to an event, however not necessarily a nurse in the structure 24/7.
Independent living can be a strong fit when:
- The individual is still able to handle personal care, medications, and mobility with little or no help.
- Driving is ending up being stressful or risky and they need transportation solutions.
- Loneliness is creeping in and social seclusion is a concern.
- The home environment has become excessive, such as stairs, backyard work, or continuous repairs.
What independent living does not do well is continuous medical management. If your parent has unsteady cardiac arrest, requires insulin modifications, or deals with complex wound care, an independent setting will likely rely greatly on outside home health nurses and frequent clinic visits. Personnel may observe that "something is off," but they are not there to handle medical crises.
A common misunderstanding is that personnel in independent living will immediately "watch" on residents' medication adherence, nutrition, and hydration. Some neighborhoods use extra cost based health checks, but the standard expectation is self-reliance. Issues can go undetected longer than households realize, particularly if the resident is private or lessening their struggles.
Assisted living: daily support and a mid level of oversight
Assisted living sits in between independent living and nursing homes. It is developed for individuals who can no longer manage securely on their own, yet do not require continuous experienced nursing care.
Residents normally live in private or semi private apartments. The structure layout may look similar to independent living, however the personnel mix and expectations vary. Assistants are offered to assist with what experts call activities of daily living: bathing, dressing, grooming, toileting, moving, and often consuming. Medication administration is frequently a significant service, with personnel arranging pill boxes, advising locals, and physically distributing medications.
Nursing presence in assisted living varies. In some states, regulations need a nurse on site for a particular number of hours daily. In others, a nurse might be shared throughout a number of structures or readily available on call. That difference matters for people with more than regular medical needs.
In practical terms, assisted living works well when somebody:
- Needs routine help with several individual care tasks, such as bathing, dressing, or getting securely in and out of bed.
- Has medication regimens that they can not dependably manage alone.
- Is at danger of falls and gains from more regular check ins.
- Has mild to moderate cognitive decrease but can still get involved meaningfully in daily decisions.
Compared to independent living, there is more structure in assisted living. Meals are usually served at set times, care tasks are arranged, and personnel documentation is more official since of regulative expectations.
Families often assume assisted living can "do everything" short of a ventilator. That is not accurate. Assisted living is not a small medical facility. Normal restrictions consist of:
- No capacity for continuous heart, oxygen, or telemetry monitoring.
- Limited capability to handle complicated behavioral issues in innovative dementia.
- Restrictions around feeding tubes, complex IV medications, or regular suctioning.
- Inconsistent capacity to handle late stage Parkinson's or other conditions that require extensive, hands on care lot of times per hour.
When requires relocation beyond what assisted living can safely offer, nursing homes (also called knowledgeable nursing facilities) go into the picture.
Nursing homes: treatment and 24/7 supervision
Nursing homes provide the greatest level of care in the basic senior care continuum except a healthcare facility. They are accredited as health care centers, staffed with nurses and aides all the time, often with on website access to physical, occupational, and speech therapy.
Residents in nursing homes typically fall under 2 broad categories. First are short stay clients who come for rehabilitation after a hospital stay, for example following a hip fracture or stroke. Second are long term citizens whose persistent conditions or practical restrictions are too extensive for assisted living.
In a nursing home, every resident has a customized care plan reviewed routinely by an interdisciplinary group. Medication management is detailed. Vital indications and weight are tracked. Lab draws, injury treatments, catheter care, and oxygen adjustments belong to routine operations.
That level of oversight is necessary for people who:
- Need skilled nursing services daily or near daily.
- Cannot dependably transfer or rearrange themselves, raising danger for pressure injuries.
- Have advanced dementia with significant behavioral issues or wandering.
- Require complex medical devices such as feeding tubes or regular IV medications.
The trade off is environment and autonomy. Nursing homes feel more scientific. Shared rooms prevail, particularly under Medicaid funding. Daily routines are shaped around personnel workflows and medical needs. Locals still have rights and choices, but that flexibility exists inside a health care framework.
One practical point: families typically ask whether moving a loved one to a nursing home indicates "giving up." In my experience, it is much better framed as matching the strength of assistance to the strength of requirement. For somebody who is risky without very close monitoring, a nursing home can lower emergency room visits, provide structure to days and nights, and alleviate family caregivers who have been running at an unsustainable pace.
Respite care: short-term relief and test drives
Respite care is the most misinterpreted piece of elderly care. Rather of being a long term positioning, respite is momentary care supplied to offer the normal caregiver a break or to bridge a transition.
Respite can take place in numerous settings:
- In home, where a paid caretaker or nurse comes for a set variety of hours or days.
- In assisted living or nursing homes, where the person remains for a limited period, often 1 to 30 days.
- In adult day programs, where the individual participates in during daytime hours only.
Families typically discover respite care after a crisis, such as a caregiver's hospitalization or burnout. Used proactively, it can avoid those crises. I have seen partners keep their loved one in the house for several years longer due to the fact that they integrated in a routine rhythm of respite, such as one weekend a month or a week each quarter.
Respite remains in assisted living likewise serve another valuable function: they let everybody see how an individual adjusts to common living without a long-term commitment. You learn how they sleep, whether they sign up with activities, and how much personnel assistance they genuinely require. That info shapes longer term choices and can correct overoptimistic or overpessimistic assumptions.
One restriction of respite care is schedule. Neighborhoods may have designated respite houses, or they may offer respite just when a regular apartment is briefly uninhabited. Planning ahead helps.
Comparing the settings side by side
Although I do not suggest basing decisions exclusively on checklists, it assists to see how these care types line up on a couple of core dimensions.
|Aspect|Independent living|Assisted living|Nursing home|| ----------------------------|--------------------------------------------|---------------------------------------------------|---------------------------------------------------|| Primary focus|Lifestyle and convenience|Assistance with day-to-day jobs and standard health needs|Comprehensive medical and personal care|| Medical staff on site|Minimal, often none on website|Aides plus restricted nursing hours|Nurses and aides 24/7|| Individual care support|Not routinely provided|Yes, set up and as needed|Yes, comprehensive and regular|| Medication management|Resident managed, some suggestions possible|Staff managed and recorded|Completely handled with pharmacy oversight|| Typical resident profile|Independent, socially oriented|Requirements assist with ADLs, some cognitive impairment|Significant medical or cognitive requirements|| House/ space type|Personal apartment or condos|Personal or semi private apartments|Personal or shared spaces, more scientific design|| Payment sources|Mostly private pay|Mainly personal pay, some waivers in some states|Mix of Medicare (brief stay), Medicaid, personal|
This table streamlines a messy reality. Laws differ by state, and specific communities stretch or narrow their service lines within those constraints. When you tour, you are not simply taking a look at the category. You are examining how that specific structure translates its role.
Signs that independent living might no longer be enough
Many households postpone transitions due to the fact that they fear distressing their loved one, or they hope that "a bit more help" will be enough. That is easy to understand. Still, particular patterns normally signal that independent living no longer matches the person's needs.
Examples consist of repeated medication mistakes, such as missed out on doses, double dosing, or confusion about brand-new prescriptions. Another red flag is increased involvement from the community's personnel. If housekeeping, dining room groups, or front desk personnel are regularly calling you about concerns, they may currently be stretching beyond what their role allows.
Frequent falls, even if minor, suggest that movement or judgment has altered. So do episodes of getting lost within the building, leaving ranges on, or mixing up day and night. When next-door neighbors begin acting as de facto caregivers, checking in numerous times a day, the plan is starting to exceed what independent living can securely support.
The natural next step for a number of these citizens is assisted residing in the same school, if offered, or in a similar neighborhood. Familiar environments ease the transition, especially for somebody with cognitive impairment.
When assisted living reaches its limits
On the surface area, assisted living may look calm and capable. Locals are dressed, public areas tidy, and staff appear attentive. Beneath, personnel may already be pressing their licensed scope of practice to keep certain homeowners stable.
Practical tipping points include:
- Recurrent hospitalizations for infections, cardiac arrest, or breathing problems regardless of excellent everyday care.
- Needs for 2 or more personnel to securely transfer the individual, particularly if those transfers occur many times a day.
- Aggressive or risky behaviors associated with dementia that put other locals or staff at risk.
- Complex medical devices that requires experienced oversight, not simply standard training.
In those situations, even the best assisted living group ultimately has to admit that a nursing home environment is much safer. This is not failure. It reflects the various legal and useful frameworks under which each type of structure operates.
An easy process for selecting the best level of senior care
Families typically request for a formula. There is no best one, however there is a procedure that regularly clarifies thinking. Use the following as a working sequence, not a stiff rulebook.
- Start with function, not age. Note what the individual can do individually, what they can do with prompting, and what they can not do even with aid. Be completely sincere about bathing, toileting, transfers, consuming, and handling medications and money.
- Identify the leading 3 safety concerns. Falls, roaming, avoiding medications, driving, cooking, or vulnerability to scams are all common. Rank them by threat and effect. This matters more than counting diagnoses.
- Map existing assistance. Who is currently helping and how often: spouse, adult kid, neighbor, paid aide, or nobody. Include travel distance, work schedules, and caregiver health. Numerous plans stop working due to the fact that they assume more family accessibility than in fact exists.
- Factor in medical complexity. Think about how often the individual sees medical professionals, whether they require regular tracking, and how rapidly they decrease when ill. A relatively stable 90 year old might fit assisted living better than a clinically fragile 70 year old.
- Weigh worths and preferences. Some older adults would accept more risk to preserve self-reliance. Others focus on security and medical backup. Put those dreams beside the truths above and ask where you can compromise and where you cannot.
When families stroll through this procedure on paper, the proper setting generally emerges. If function is high and safety issues are mostly about social seclusion, independent living might be sufficient. If individual care requirements and medication intricacy dominate, assisted living ends up being attractive. When safety and medical complexity are both high, nursing home level care, perhaps preceded by a respite stay, should have major consideration.

How cost and financing differ throughout settings
The monetary side of elderly care frequently surprises people more than the psychological side. A couple of assisting concepts assist set reasonable expectations.
Independent and assisted living are largely personal pay in the United States. Regular monthly fees often vary from a couple of thousand dollars to upper four figures or more, depending on area, home size, and service levels. senior living Some states use Medicaid waiver programs that fund assisted living for eligible low earnings citizens, but slots are restricted and waiting lists common.
Nursing homes blend 3 primary payers: Medicare, Medicaid, and personal pay. Medicare covers short term competent stays after qualifying hospitalizations under particular guidelines. It does not pay indefinitely for long term custodial care. Once Medicare protection ends, homeowners either pay independently or, if eligible, shift to Medicaid. Medicaid becomes the main payer for a big share of long stay residents.
Respite care can be paid out of pocket, through certain insurance coverage plans, or in limited cases through veteran benefits or local relief programs. Expenses differ widely by setting, but daily rates in neighborhoods typically line up with their basic everyday room and board plus care fees.
Before touring neighborhoods, it is smart to collect:
- Rough monthly spending plan from earnings and assets.
- Insurance details: Medicare Benefit vs standard Medicare, any long term care insurance, veteran status.
- A sense of the length of time current resources must last, particularly if one partner is much healthier and will outlive the other.
That financial map will not determine every decision, yet it avoids heartbreaking surprises months into a placement.
Using respite care strategically, not simply in crisis
Families who thrive over the long term typically use respite care before they feel desperate. A daughter who cares for her mother in your home may set up a week of respite in assisted living two times a year, timed to her own busiest work periods. A kid might generate in home respite every Saturday afternoon so he can attend his kids' video games or simply rest.
These planned breaks serve several functions. They protect the main caregiver's health, give the older adult exposure to different environments and individuals, and test how well current support arrangements are working. If your loved one struggles significantly during a brief respite stay, that is data. It might imply they need a various sort of setting faster than anticipated, or that more gradual shaping of expectations is required.
I have also seen respite end up being a bridge during significant life occasions, like a caretaker's surgery or moving. Instead of hurrying into an ill fitting long term placement, households use a 30 day respite stay while they sort out what comes next. That buffer decreases pressure and enables more thoughtful choices.
When siblings and families disagree
Disagreements about elderly care are almost inevitable. One brother or sister may promote a nursing home, another insist that "Mom guaranteed she would never go to a facility." Beneath those positions typically lies a mix of guilt, worry, and different memories of childhood roles.
What assists is anchoring discussions in observable realities rather than analyses. Rather of "She is fine in your home," define the number of times somebody helps her shower each week, how many falls happened in the last month, or how typically the stove was left on. Concrete data softens absolutist positions.
Bringing in a neutral expert evaluation can likewise break stalemates. Geriatric care supervisors, social workers connected to centers or healthcare facilities, or palliative care groups can review medical records, observe function, and suggest appropriate levels of care. When a non family professional states, "Based on her existing needs, assisted living would be hazardous, she qualifies for nursing home care," it carries weight.
If possible, include the older adult truthfully. Sugarcoating often backfires. Numerous seniors value being treated as partners rather than as issues to be resolved in trick. The way you frame alternatives matters. Phrases like "We wish to find a location where you are safe and surrounded by people, and where we can visit as children, not just as caretakers" often land better than "You can not live alone any longer."
Final ideas: matching individual, requires, and setting
All of these care settings exist for a factor. Independent living supports way of life and community when maintenance and driving ended up being too heavy. Assisted living bridges self-reliance and hands on assistance, stabilizing life for those who need daily assistance but not consistent treatment. Nursing homes concentrate knowledgeable resources around those who are most clinically and functionally vulnerable. Respite care secures caretakers and gives everyone space to breathe.
The right option is the one that reasonably attends to existing risks, expects near term modifications, respects the older grownup's worths as much as possible, and fits within financial and household limits. Perfect solutions are unusual. Good enough options, revisited and adjusted in time, are not only possible however common.
Elderly care is not a one time choice. It is an evolving process. The more you comprehend what each setting really provides, the much better equipped you are to make each step of that journey with clearness and compassion.
BeeHive Homes of Volcano Cliffs provides assisted living care
BeeHive Homes of Volcano Cliffs provides respite care services
BeeHive Homes of Volcano Cliffs supports assistance with bathing and grooming
BeeHive Homes of Volcano Cliffs offers private bedrooms with private bathrooms
BeeHive Homes of Volcano Cliffs provides medication monitoring and documentation
BeeHive Homes of Volcano Cliffs serves dietitian-approved meals
BeeHive Homes of Volcano Cliffs provides housekeeping services
BeeHive Homes of Volcano Cliffs provides laundry services
BeeHive Homes of Volcano Cliffs offers community dining and social engagement activities
BeeHive Homes of Volcano Cliffs features life enrichment activities
BeeHive Homes of Volcano Cliffs supports personal care assistance during meals and daily routines
BeeHive Homes of Volcano Cliffs promotes frequent physical and mental exercise opportunities
BeeHive Homes of Volcano Cliffs provides a home-like residential environment
BeeHive Homes of Volcano Cliffs creates customized care plans as residents’ needs change
BeeHive Homes of Volcano Cliffs assesses individual resident care needs
BeeHive Homes of Volcano Cliffs accepts private pay and long-term care insurance
BeeHive Homes of Volcano Cliffs assists qualified veterans with Aid and Attendance benefits
BeeHive Homes of Volcano Cliffs encourages meaningful resident-to-staff relationships
BeeHive Homes of Volcano Cliffs delivers compassionate, attentive senior care focused on dignity and comfort
BeeHive Homes of Volcano Cliffs has a phone number of (505) 302-1919
BeeHive Homes of Volcano Cliffs has an address of 6230 Montaño Rd NW, Albuquerque, NM 87120
BeeHive Homes of Volcano Cliffs has a website https://beehivehomes.com/locations/volcano-cliffs/
BeeHive Homes of Volcano Cliffs has Google Maps listing https://maps.app.goo.gl/vC78eXZrUYuJ298v9
BeeHive Homes of Volcano Cliffs has Instagram page https://www.instagram.com/beehivealbuquerquewest
BeeHive Homes of Volcano Cliffs has an TikTok page https://www.tiktok.com/@beehivehomesalbuq
BeeHive Homes of Volcano Cliffs won Top Assisted Living Homes 2026
BeeHive Homes of Volcano Cliffs earned Best Customer Service Award 2025
BeeHive Homes of Volcano Cliffs placed 1st for Senior Living Communities 2026
People Also Ask about BeeHive Homes of Volcano Cliffs
What is BeeHive Homes of Volcano Cliffs Living monthly room rate?
Our base rate is $7,100 per month. We do an assessment of each resident's needs upon move-in, so each resident's rate may be slightly higher. However, there are no add-ons or hidden fees. We also charge a one-time community fee of $2,000 at move-in
Does Medicare or Medicaid pay for a stay at Bee Hive Homes?
Medicare pays for hospital and nursing home stays, but does not pay for assisted living. Some assisted living facilities are Medicaid providers, but we are not. We do accept private pay, long-term care insurance, and we can assist qualified Veterans with approval for the Aid and Attendance program
Do we have a nurse on staff?
We do have a nurse on contract who is available as a resource to our staff but our residents' needs do not require a nurse on-site. We always have trained caregivers in the home and awake around the clock
What can you tell me about the food at Bee Hive?
You have to smell it and taste it to believe it! We use dietitian-approved meals with alternates for flexibility, and we can accommodate needs for different texture and therapeutic diets. We have found that most physicians are happy to relax diet restrictions without any negative effect on our residents
Do we allow pets?
We do allow small pets as long as the resident is able to care for them. State regulations also require that we have evidence of current immunizations for any required shots
Where is BeeHive Homes of Volcano Cliffs located?
BeeHive Homes of Volcano Cliffs is conveniently located at 6230 Montaño Rd NW, Albuquerque, NM 87120. You can easily find directions on Google Maps or call at (505) 302-1919 Monday through Sunday 10:00am to 7:00pm
How can I contact BeeHive Homes of Volcano Cliffs?
You can contact BeeHive Homes of Volcano Cliffs by phone at: (505) 302-1919, visit their website at https://beehivehomes.com/locations/volcano-cliffs/ or connect on social media via Instagram Facebook or TikTok
K Style Kitchen provides a convenient local restaurant where families supporting loved ones through Assisted living memory care senior care elderly care and respite care can enjoy an outing together.